

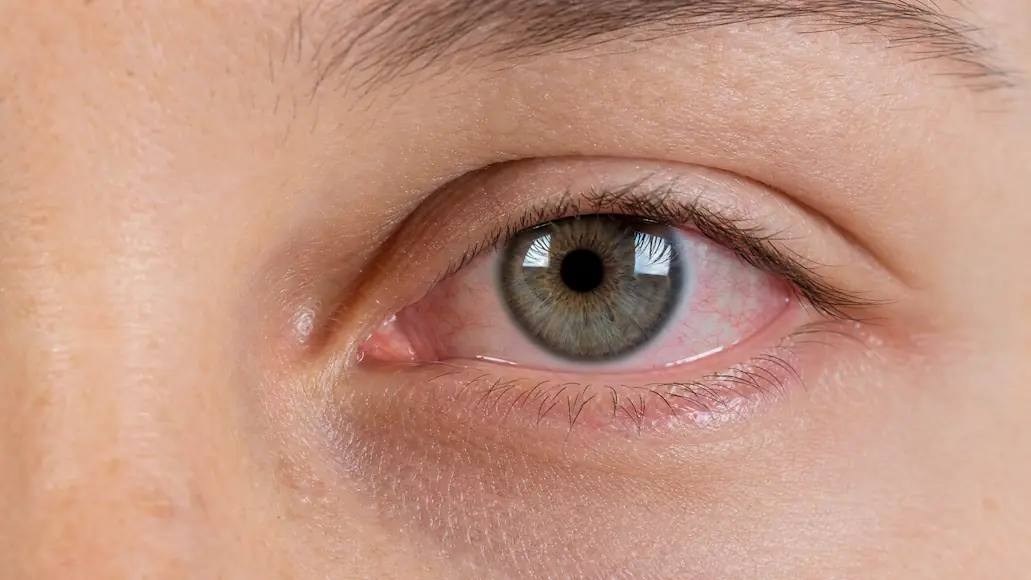
Amniotic membrane transplantation places a thin layer of donated placental tissue over a damaged eye surface, to shield it while it heals. It is used for corneal ulcers that will not heal, chemical burns and severe surface disease. Mr Arthur Okonkwo, Consultant Ophthalmologist, assesses and treats these problems at St James Laser Vision Clinic in Leeds.
The membrane comes from consenting mothers after a planned caesarean section, and every donor is screened by NHS Blood and Transplant. Treatment takes 20 to 45 minutes under local anaesthetic, usually as a day case.
Is an Eye Surface Problem Slow to Heal?
Book at St James if an ulcer, burn or surface problem is slow to heal. Bring a list of every eye drop used in the past 3 months.
Prefer to call? 0113 460 1923, Monday to Friday, 9am to 5pm
What Is Amniotic Membrane Transplantation?
Amniotic membrane is the inner lining of the placenta, and it carries natural proteins that help calm inflammation and scarring. On the eye, it acts as a living dressing while the surface cells regrow underneath.
Frozen grafts come in 2 x 2 cm, 3 x 3 cm and 5 x 5 cm sheets, trimmed to fit the damaged area. A graft can dissolve within 1 to 2 weeks, or be stitched or glued in as a lasting graft. In some cornea stem cell grafts it is also used as a support layer, as set out in NICE guidance HTG139.
Eye Surface Symptoms and When to Get Urgent Help
A red eye that hurts in light, or with any change in sight, means 999 or A&E. Any chemical in the eye is an eye injury emergency: keep rinsing with clean water for at least 20 minutes on the way to help.
| Your symptom | Possible cause | What to do |
|---|---|---|
| Chemical such as bleach in the eye | Chemical burn | Rinse for 20 minutes, then 999 or A&E |
| Painful red eye with a white spot | Corneal ulcer from infection | Same-day eye unit, A&E or NHS 111 |
| Sore eyes with a spreading rash after a new medicine | Possible Stevens-Johnson syndrome | Call 999 or go to A&E |
| Red, sticky eyes that do not settle, lids turning in | Possible mucous membrane pemphigoid | Ask your GP or optician for a referral |
| Pain, redness or blurring worsening after treatment | Infection or inflammation | Ring the eye team the same day |
| Confusion, shivering, fast breathing or blotchy skin | Possible sepsis | Call 999 or go to A&E |
The signs of sepsis need 999, and a chemical injury goes to A&E before any graft is planned.
Conditions Mr Okonkwo Treats with Amniotic Membrane
- Persistent corneal ulcers: sores that stay open despite treatment, covered on corneal infections and ulcers.
- Chemical and heat burns: the membrane covers the raw surface once the eye has been rinsed for at least 20 minutes and assessed.
- Stevens-Johnson syndrome: can cause eye pain, light sensitivity and long-term sight problems. See the NHS Stevens-Johnson syndrome page.
- Ocular mucous membrane pemphigoid: a rare scarring disease affecting about 8 in 10 million people a year.
- Severe dry eye: a short-term cover giving 6 weeks to 3 months of relief, with wider options on dry eye procedures.
- Healing after surface surgery: large areas left after pterygium excision.
- Corneal scarring: the membrane protects a scarred surface while it settles.
Treatment Options: How the Membrane Is Used
There are 3 ways of applying the membrane, depending on whether the eye needs a short-term dressing or new tissue.
Membrane Under a Bandage Contact Lens
A small piece rests on the cornea, held by a soft contact lens. It suits dry eye, giving 6 weeks to 3 months of relief, and is placed in clinic with no theatre visit.
Membrane Stitched or Glued as a Temporary Cover
For an ulcer or burn, the membrane is secured over the damaged area in a 20 to 45 minute day-case procedure under local anaesthetic. It dissolves over 1 to 2 weeks, and sight is blurred while it is in place.
Membrane as a Lasting Graft
Here the membrane replaces missing surface tissue and becomes part of the healed eye, for deeper damage or rebuilding after surgery on the conjunctiva. Theatre time is again 20 to 45 minutes, with close follow-up. Infection is the main risk, which is why NHS Blood and Transplant screens each donor.
Not Sure Whether a Membrane Graft Is Right for You?
Mr Arthur Okonkwo will explain whether amniotic membrane transplantation suits your eye at your consultation.
Prefer to call? 0113 460 1923, Monday to Friday, 9am to 5pm
Why Patients Choose Mr Okonkwo
- Eye surface focus: a Leeds Consultant Ophthalmologist, fellowship-trained twice, specialising in corneal disease.
- Transplant research degree: MRes in transplantation (Distinction). Also FRCOphth, CertLRS, PgDip (CRS) and PgCert (MedEd).
- Training: academic ophthalmology posts in Leeds and Manchester, followed by two fellowships: Moorfields Eye Hospital, London, and Melbourne’s Royal Victorian Eye and Ear Hospital.
- NHS post: leads NHS and private clinics within Leeds Teaching Hospitals NHS Trust.
- Teaching: Honorary Senior Lecturer at the University of Leeds.
- Research: over 30 peer-reviewed publications, with corneal transplantation one of his 3 research themes.
Donor Tissue: Where the Membrane Comes From and How It Is Screened
The membrane is collected from living donors after a planned caesarean section, tissue that would otherwise be thrown away, at only a few UK hospitals. The membrane is separated, rinsed, cleaned with antibiotics and frozen, then held in quarantine until the donor has been medically cleared.
Each donor has blood tests for HIV, hepatitis B, hepatitis C, HTLV and syphilis. Every donation is screened for bacteria and fungi, and a graft is only released once results show it is safe. Rejection is rare, because the tissue lacks most of the markers that trigger it.
Alternatives to Amniotic Membrane Transplantation
Simpler steps often come first for a failing eye surface.
- Intensive lubricants: frequent drops to keep the surface wet.
- Steroid drops: to calm inflammation.
- Bandage contact lens alone: a soft lens shields the cornea while it heals.
- Serum eye drops: made from your own or a donor’s blood, for severe dryness.
- Corneal or limbal grafts: for deeper or lasting damage. See corneal transplantation.
Your Pathway, Step by Step, from the First Appointment
- Referral: a GP, optician or the Leeds eye casualty can refer you, though a letter is not always needed privately. A fresh chemical injury goes to A&E first.
- Assessment: a longer first appointment at St James Laser Vision Clinic, with history, examination, scans and a dye drop that shows damaged cells.
- Planning: Mr Okonkwo explains whether a bandage under a lens, a stitched cover or a lasting graft fits your eye, and you agree the plan before a date is set.
- Treatment day: local anaesthetic, 20 to 45 minutes, then home with a pad or shield, with theatre cases at [to confirm].
- Follow-up: checks at St James while the surface heals, close and frequent at first.
Recovery and Risks After Amniotic Membrane Transplantation
A temporary membrane dissolves over 1 to 2 weeks. Until then, looking through it is like looking through frosted glass, and sight then depends on how deep the original damage went.
Covering exposed nerve endings often eases the pain of an ulcer or burn. A corneal ulcer can still scar even with correct treatment.
| Treatment | Hospital stay | Example risk |
|---|---|---|
| Membrane under a bandage contact lens | None, given in clinic | Relief may fade after 6 weeks to 3 months |
| Membrane stitched or glued as a cover | Day case, 20 to 45 minutes | Blurred, frosted vision until it dissolves in 1 to 2 weeks |
| Membrane as a lasting graft | Day case | Infection, reduced by donor screening |
| Any of these, for an ulcer | As above | Scarring that may still affect sight |
Severe eye infection is one reason for a later cornea transplant, which waits until the eye has been free of infection for some time.
Where Mr Okonkwo Sees Patients
The clinic is in the Gledhow Wing, Floor 4, of St James’s University Hospital.
| Location | Address |
|---|---|
| St James Laser Vision Clinic | Floor 4, Gledhow Wing, St James’s University Hospital, Beckett Street, Leeds LS9 7TF |
| Theatre for amniotic membrane transplantation | St James’s University Hospital, Beckett Street, Leeds LS9 7TF |
The practice line, 0113 460 1923, is answered Monday to Friday from 9am to 5pm. Evenings and weekends, NHS 111 or 999 can help with urgent eye problems.
FAQs About Amniotic Membrane Transplantation
Is amniotic membrane transplantation a major operation?
No. It takes 20 to 45 minutes under local anaesthetic, usually as a day case. A bandage version can be placed in clinic.
How long is recovery after an amniotic membrane graft?
A temporary membrane dissolves over 1 to 2 weeks. Full recovery depends on the ulcer, burn or disease underneath.
Can I drive after amniotic membrane treatment?
Not on the day, and not for the 1 to 2 weeks the membrane blurs sight. Wait until your vision meets the legal standard and your doctor agrees.
Can the ulcer or surface damage come back?
It can. Ulcers can scar despite correct treatment, and pemphigoid is held in remission rather than switched off for good.
What can be tried instead of a membrane graft?
Lubricants, steroid drops, bandage contact lenses and serum drops, with corneal and limbal grafts kept for deeper damage.
Who donates the amniotic membrane?
Mothers having a planned caesarean section donate it, and NHS Blood and Transplant then screens and processes it.
Will the membrane stay on my eye for good?
Usually not. As a dressing it dissolves within 1 to 2 weeks. As a lasting graft, it becomes part of the healed surface.
Why is my vision cloudy after the membrane is placed?
The membrane is translucent, not clear, and vision improves as it dissolves over 1 to 2 weeks.
Is there a risk of rejecting donor membrane?
Rejection is uncommon, because the tissue lacks most rejection markers. Infection is the bigger concern, so NHS Blood and Transplant screens donors for HIV and hepatitis.
Does the procedure hurt?
Local anaesthetic numbs the eye, and the procedure often eases pain afterwards.
Quick Info
What is it?
A donated membrane placed over the cornea as a cover or graft
Who is it for?
Non-healing ulcers, chemical or heat burns, severe surface inflammation and scarring
How long does it take?
About 20 to 45 minutes
Hospital stay
Usually a day case under local anaesthetic
Recovery
A temporary membrane dissolves over 1 to 2 weeks
Ready to Get Started?
Book a consultation to discuss your symptoms and treatment options.
Book a Consultation with Mr Arthur Okonkwo
Book at St James if an ulcer, burn or surface problem is slow to heal. Bring a list of every eye drop used in the past 3 months.
- Phone: 0113 460 1923 (weekdays, 9am to 5pm)
- Online: a membrane assessment request, or questions first
A more painful, redder or blurrier eye needs your GP, optician or NHS 111 urgently. A chemical in the eye, sudden sight loss or signs of sepsis mean 999 or the closest emergency department.